
2025-2026 Preclinical Drug Research Steven Van Cruchten
PRECLINICAL DRUG RESEARCH
PHARMACOKINETICS (PP 5)
Importance: big factor in drug failure (when you detect bad PK in phase 2 or 3 it will cost u a lot)
Remember: fail fast = fail cheap!
INTRODUCTION
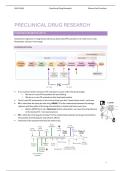
• It’s a current trend to introduce PK-evaluation as part of the chemical design: Pharmacokinetics
o We do an in vitro PK-evaluation for lead finding Re
Pharmacokinetics
o We do an in vivo PK-evaluation after lead optimization of
• There’s also PK assessment in the clinical trials (you don’t want failure here!): red arrow
• PK = what does the body do with drug (ADME)? It’s the relationship between the dosage
regimen and the profile of the drug concentration in blood and tissue over time input
o Before ADME there is L = liberation (before absorption, e.g. does the drug dissolve output
in the stomach?) = not used anymore
• PD = what does the drug do to body? It’s the relationship between the drug concentration-
time profileDetailed R&D
and therapeutic positioning
and adverse effects
• Overview of the assessments that we need to do:
Re
Pharmacodynamics pr
1
,2025-2026 Preclinical Drug Research Steven Van Cruchten
ADME PROPERTIES
ABSORPTION
• Bioavailability = what is taken up into the bloodstream (some of the compound will go to the feces,
get metabolized by the enterocytes or liver…)
• IV injection of the compound gives a bioavailability of 100%
DISTRIBUTION
• Distribution = the process by which a drug diffuses or is transferred from IV to EV space (body tissue)
o High volume of distribution: compound distributes to the tissues
o Low volume of distribution: compound stays in the circulation
o Depending on the target, this is something that we want or don’t want (e.g. we don’t want a
platelet aggregation inhibitor to distribute to tissues)
• Important factors that can influence the distribution of a drug:
o Blood flow: when the person has a lower blood flow à drug will not get to liver quickly for
metabolization à the plasma concentration is higher à give a lower dose
o Ionization: dependent on pKa and pH
o Protein binding: if the drug is prone to binding proteins, like albumin
§ It will diffuse less to the tissue and stay in blood longer à the plasma concentration
is higher
§ BUT often the free fraction is the working fraction, binding to albumin will cause a
less accessible fraction of the drug
§ In principle, a drug bound to a protein stays in the bloodstream, but this is not
always true à you should look at the Vd
o Distribution Volume (Vd) = the theoretical volume to which a drug disperses in order to produce
the observed plasma concentration (e.g. when the dose of drug is high, but the plasma
concentration is low, then the Vd is high)
!"#$
𝑉! = %&'#(')"*)$+,'+-"* 𝑖𝑛 𝐿/𝑘𝑔
à Vc (central distribution volume) = hypothetical volume into which a drug initially distributes.
This compartment can be thought of as the blood in vessels and in tissues which are highly
perfused (Vc = dose/peak serum level)
à Vt (peripheral distribution volume) = the volume into which a drug is distributed in all tissue
spaces outside the central compartment
o Factors that influence Vd:
§ Timing of measurements (where and when you measure Vd): in reality, the
compound might not be distributed equally among tissue and it takes time for the
drug to distribute around the body, the plasma concentration after minutes of
administration will be different from the Cp hours later. Take the time you administer
the dose and measure outcome into account!
§ The protein-binding and tissue-binding of a compound (depends on drug
properties à Lipinsky’s rule of 5)
§ The patient-specific factors (physiological factors):
• Age: when we get older the muscle/fat ratio decrease, so Vd decreases
• Gender: women have less water so generally a lower Vd
• Body muscle/ fat ratio: muscle is more water so higher Vd
• Level of hydration and water distribution (e.g. oedema, pregnancy…)
2
,2025-2026 Preclinical Drug Research Steven Van Cruchten
METABOLISATION
• Often the metabolite also has an effect:
o Bioactivation = metabolite is the active form of the compound and will have an effect in the
body. This can be a therapeutic effect or a toxic effect.
o Biotransformation = the compound is changed from hydrophobic to hydrophilic to facilitate the
elimination from body
ELIMINATION
• Drugs are cleared primarily by the liver and kidneys; urinary excretion is a major route of elimination
for metabolites and unchanged drugs
o Metabolization of drug in liver/ kidneys: the higher the metabolization rate, the more the drug
gets hydrophilic for a quicker elimination.
o Most drugs are eliminated by a first-order process: the amount of drug eliminated is directly
proportional to the serum drug concentration
o Clearance (Cl) = the rate at which elimination happens = first-order process (amount of drug
removed, depends on the concentration)
𝐶𝑙 = 𝐾𝑒𝑙 ∙ 𝑉! = 0,693 ∙ 𝑉! /𝑡./0 with Kel = elimination constant
o Half-life (t1/2) = time where 50% of the concentration of the drug remains in your body. This is
very important à ideally, we want a long t1/2 so patient only has to take the drug once a day =
better compliance. The longer the t1/2 the longer the plasma concentration stays high J
o Css = steady state à we want to obtain this so that the plasma concentration stays the same
over time J we want this ofcourse
§ 1x t1/2 = 50% initial concentration
§ 5x t1/2 = +- 3% initial concentration
à If you administer the drug after 5x t1/2, the concentration is too small for
accumulation. The dose interval needed to reach the Css < 4 or 5 times the t1/2
§ If this is the case, there will be accumulation of the drug until a plasma
concentration equilibrium is reached = steady state
§ It takes 5 times the t1/2 to reach this steady state L we will give a loading dose (a
higher dose that fill the distribution volume to the steady state is reached
immediately) = 𝑄 = 𝐶𝑠𝑠 ∙ 𝑉!
• Vd is used to calculate this loading dose!
§ To keep the plasma concentration at the steady state, we need to give a
maintenance dose = 𝑄 = 𝐶𝑠𝑠 ∙ 𝐶𝑙𝑒𝑎𝑟𝑎𝑛𝑐𝑒
• Clearance is used to calculate the maintenance dose!
• The prof showed a paper: The Importance of the Human Mass Balance Study in Regulatory
Submissions
o Main message: the mass balance study is the only study that we can do to assess how a
compound is eliminated and to what extent (gives information about the elimination pathways)
o How does it work? The compound is linked to a weak radio-active ligand which is given to
volunteers. Now, we can trace the compound in the different matrices (blood, urine, feces)
o This gives us a view on the major route of elimination for this compound. In most cases we
expect this to be the kidney but if we have a strong metabolizer, the liver will be important and, in
some cases, we have fecal elimination!
o Important information to be able to set a dose in the clinical trial
3
, ADME compartments
2025-2026 Preclinical Drug Research Steven Van Cruchten
OVERVIEW ADME COMPARTMENTS
Pharmacological effect
Toxicological effects
Pharmacokinetics: some basics
Pharmacokinetic modeling: one-compartment model
PHARMACOKINETIC MODELING
Drugs with rapid equilibration with peripheral tissues are best described with a one-compartment model
• One-compartment model: the drug distributes instantly and
Yields a straight line
uniformly throughout the body as if it were one single, well-mixed when using a log scale
compartment. When the drug is administered, we get a peak on the y-axis
plasma concentration which will go down over time because of
elimination (very easy model). If a drug rapidly equilibrates with some basics
Pharmacokinetics:
the tissue compartment, the much simpler one-compartment
model can be used, which considers onlyPharmacokinetic
the apparent volume modeling: of two-compartment model
distribution, Vd. Drugs with slow equilibration with peripheral tissues are best described with a two-compartment model
• Two-compartment model: the drug first distributes rapidly in a Yields a biphasic line when
using a log scale on the y-axis
central compartment (blood andAll well-perfused organs)
drugs initially distribute into aand then
central compartment (Vc) before distributing
Distribution phaseinto
α the peripheral
compartment
more slowly into a peripheral (tissue) (Vt). If a drug rapidly
compartment. equilibrates with the tissue compartment, the much simpler
The plasma
one-compartment model can be used, which considers only the apparent volume of distribution,
Elimination phase β Vd.
concentration will first decrease because the drugs is distributed
to the tissue compartments. After it will go down over time Elimination phase g
because of elimination (most often the case). During the initial,
rapidly declining distribution phase, drug is moving from the
central compartment to the tissue compartment.
During the initial, rapidly declining distribution phase, drug is moving from the central compartment to
the tissue compartment.
DRUG PROPERTIES & PK CHARACTERISTICS
Elimination of drug is the predominant process during the second phase of the biphasic plot.
Because elimination is a first-order process, the log plot of this phase is a straight line.
• This graph is very important for the exam! Here, we see the relationship between the different drug
properties and how they’re linked to one another:
4


