
xxx
NUR245 Lecture Week Three: Liver
Cirrhosis, Peripheral Artery Disease
Cirrhosis = bulk of next exam
PAD = limited questions
Liver Cirrhosis
*** no such thing as acute liver cirrhosis ***
only way to fix cirrhosis is with a liver transplant; it’s incurable – therefore,
we’re treating the symptoms and managing the complications
#1 cause: alcohol abuse (social death prior, then medical death –
‘they did it to themselves’) incredibly painful death
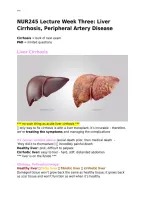
Healthy liver: pink, difficult to palpate
Cirrhotic liver: easy to feel – hard, stiff, distended abdomen
*** liver is on the R/side ***
Etiology, Pathophysiology:
Healthy liver fatty liver fibrotic liver cirrhotic liver
Damaged tissue won’t grow back the same as healthy tissue; it grows back
as scar tissue and won’t function as well when it’s healthy
,xxx
Most common causes: chronic hepatitis B, C + chronic ETOH abuse, biliary
cirrhosis
Other causes very extreme dieting, malabsorption, obesity
Biliary cirrhosis autoimmune disorder – body is attacking the bile duct
Primary sclerosing cholangitis scarring, inflammation of bile ducts lead to
liver damage
Cardiac cirrhosis hepatomegaly s/t extreme R/side HF (rare but can
happen)
Early Manifestations:
*** fatigue, tiredness, enlarged liver, weakness (VAGUE)
ALT, AST normal until late stage liver disease (doesn’t compensate yet)
elevated in later stages
Diagnosis occurs with advanced liver disease
Late Manifestations:
Resulting from liver failure + portal hypertension
jaundice, peripheral edema, ascites
skin lesions, hematologic problems, endocrine problems, peripheral
neuropathies
Liver shrinks and becomes nodular
, xxx
Jaundice is a result of inability to break down RBC/bilirubin can’t be
conjugated and excreted into the small intestine
*** auto-anticoagulated (increased PTT, aPTT, INR like they’re on an
anticoagulant) and thrombocytopenic high risk of bleeding to death *** -
we do not want them on blood thinners (warfarin, ASA, Plavix, heparin,
lovenox, ibuprofen, Motrin, Eliquis)
NSAIDs increase risk of gastric bleeding – do not give it!
pain? Give APAP – limit amount (metabolized in liver), give low dose
Liver can’t metabolize aldosterone – K+ loss, low sodium,
hypoalbuminemia
intervention: low sodium, low protein diet (albumin = protein)
Males grow breasts, women lose periods
*** portal HTN: non-cardio-selective BB (propranolol) ***
Esophageal and gastric varices are ultimately the cause of death for these
patients
Treat the symptoms with lactulose


